
OOOPDS — Orthopedic Operation and Object Planning Digital System
Do the operation once on screen. Then do it once for real.
OOOPDS turns a patient's own CT or MRI data into a scaled 3D model, then lets the surgeon work on it before the case: reduce the fracture, plan the screw path, shape the plate, print it.
FDA 510(k) cleared: K254214 (opens in a new tab) (decision date 15 September 2026, product code LLZ) · TFDA Class II Medical Device MOHW-MD-No. 007110
What it is
Orthopedic planning software, developed in Taiwan
OOOPDS — the Orthopedic Operation and Object Planning Digital System — is a 100 % domestically developed orthopedic surgical planning software, licensed by the Ministry of Health and Welfare (TFDA). It brings 2D and 3D medical imaging, surgical simulation and 3D printing together in one system, so patient-specific planning happens in a single place instead of across three.
From DICOM data to a model you can operate on
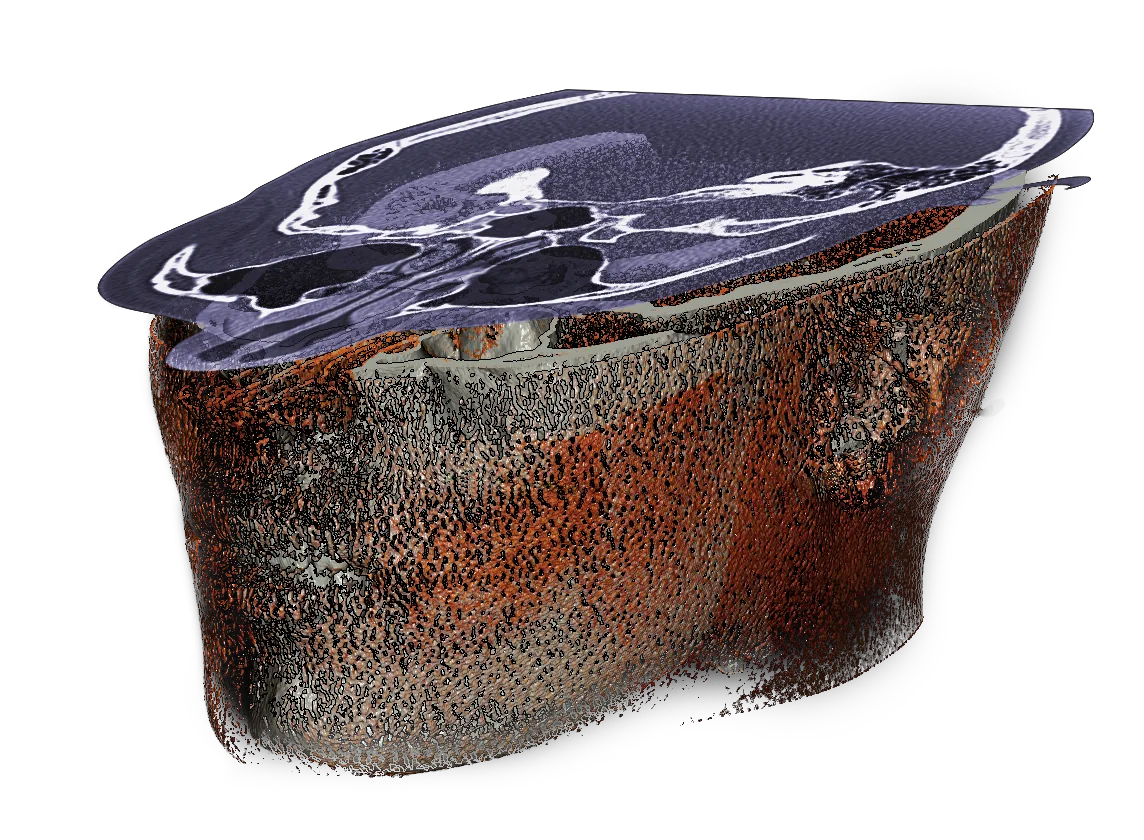
OOOPDS loads and processes 2D images in DICOM format — the global standard for medical imaging — and reconstructs them into a 3D model held at the patient's real scale, overlaid and aligned with the anatomy it came from. Nothing is approximated from a textbook: the model is that patient's bone.
Finished objects export as .stl, .ply or .obj, which is what makes the step from planning to a printed model or template a file transfer rather than a project.
- Multi-directional 2D cross-sections along the X, Y and Z axes, read alongside the 3D view
- Interactive 3D models that can be rotated, cut and separated for anatomical visualization
- Planning, simulation and printing in one workflow, from DICOM import through to the file that goes to the printer
Preoperative planning
Analyze the injury and simulate the operation before the case.
3D printing integration
Modeling and printing give a tangible spatial reference for where the bone fragments sit.
Customized bone plate design
Everyone's skeleton is different. Patient data goes in and a plate designed to that anatomy comes out.
One system, three fields
Orthopedic, spinal and dental planning run on the same software, the same imported data and the same set of tools.
Preoperative planning
Personalised planning for every patient
OOOPDS turns raw imaging into a plan the team can look at together, specific to the patient in front of them.
Five tools that do most of the work
From trauma to spine and dental cases, the planning suite covers the sequence a surgeon actually follows: understand the anatomy, put the pieces back, choose the hardware, and plan the path to it. Planning results can be exported and discussed by the whole surgical team, and shown to the patient, before the day of the operation.
- 2D/3D visualization — switch between cross-sections on the X, Y and Z axes and a fully interactive reconstruction
- Fracture simulation — move fragments by hand, or apply auto-symmetry against the healthy side, to find the alignment
- Implant simulation — choose screws and plates and place them, adjusting angle, depth and position as you go
- Customized plate design — design the plate on the reduced fracture and export it straight for printing
- Puncture and screw trajectory planning — axial, sagittal and coronal views with the 3D overlay
Inside the software
What the simulation actually looks like
Each clip below is recorded from OOOPDS itself, working on real imported patient data. No step is a mock-up of the interface — this is the software a surgeon sits in front of the evening before the case.
Manual fracture reduction
An accident rarely produces one clean break. Fragments are separated and moved by hand in 3D to plan the reduced position.
SI screw locking
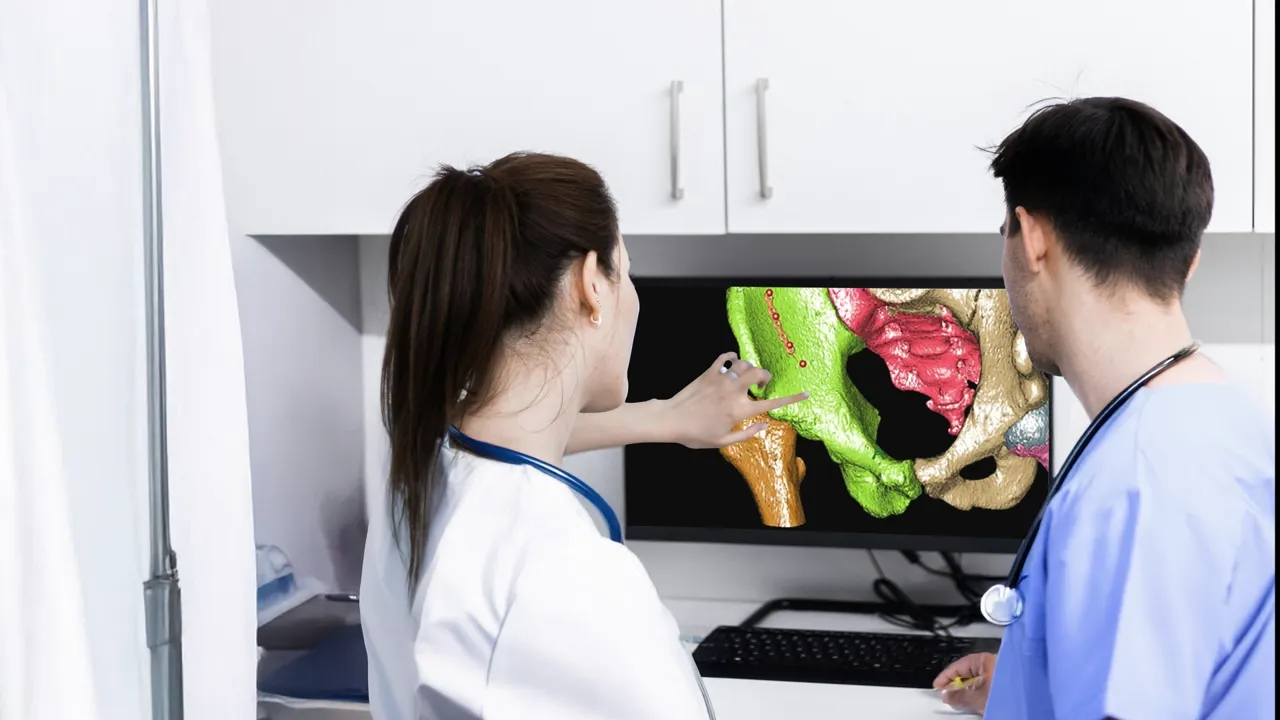
The same simulation applies to the pelvis. Against the 3D X-ray image the surgeon finds a workable locking path across the sacroiliac joint and confirms the screw's diameter and length before ordering it.
Spinal puncture path
Proportional 3D images read together with X-ray and 2D cross-sections, so the entry point, angle, length and depth can be planned in relation to the neurovascular structures.
Spine pedicle screw simulation
The patient's DICOM data is imported and the pedicle screws analyzed in place: diameter and length are confirmed on the model, and the connecting rods are generated automatically once the screws are set.
Implant screw planning
For dental work, imported DICOM data of the affected area is converted to 3D, the dental arch curve is set, and the chosen implant is locked in with its spatial position adjusted in simulation.
Segmentation and auto-reduction
Automatic bone segmentation, cutting and 3D object modeling, plus manual and automatic symmetric reduction — which mirrors the intact side to show where the broken one should end up.
System tools
The tools around the simulation
Image adjustment switches between skin and bone tissue, converts 2D brightness and tunes the 3D reconstruction threshold. Area separation splits, merges, hides and rebuilds each region of bone fragments. Meshing turns integrated regions into surface triangular meshes for export. The brush annotates directly on the image, which turns the same window into a teaching surface. Measurement covers length, angle, the angle between two segments, area, and volume and bone density on the 3D view.
3D printing
Turning data into something you can hold
A screen shows a surgeon the anatomy. A printed model lets them turn it over in their hands. OOOPDS supports the whole path — import the DICOM data, build and adjust the model, export it, print it — so the object that reaches the table came from this patient's scan and nothing else.
Three steps, one file
3D printing builds a physical object from a digital model by adding material layer upon layer. In medicine that means patient-specific bones, organs, implants and surgical guides — and in OOOPDS the digital model is the same one the surgeon has just planned on.
- Data upload and 3D modeling — DICOM data from CT, MRI or X-ray becomes a model of that patient's structure
- Customization and design — bone plates, surgical guides and implant designs are shaped to fit before anything is made
- Printing — the model is printed in biocompatible material and used in theater as a reference or a guide

The model goes into theater with the team
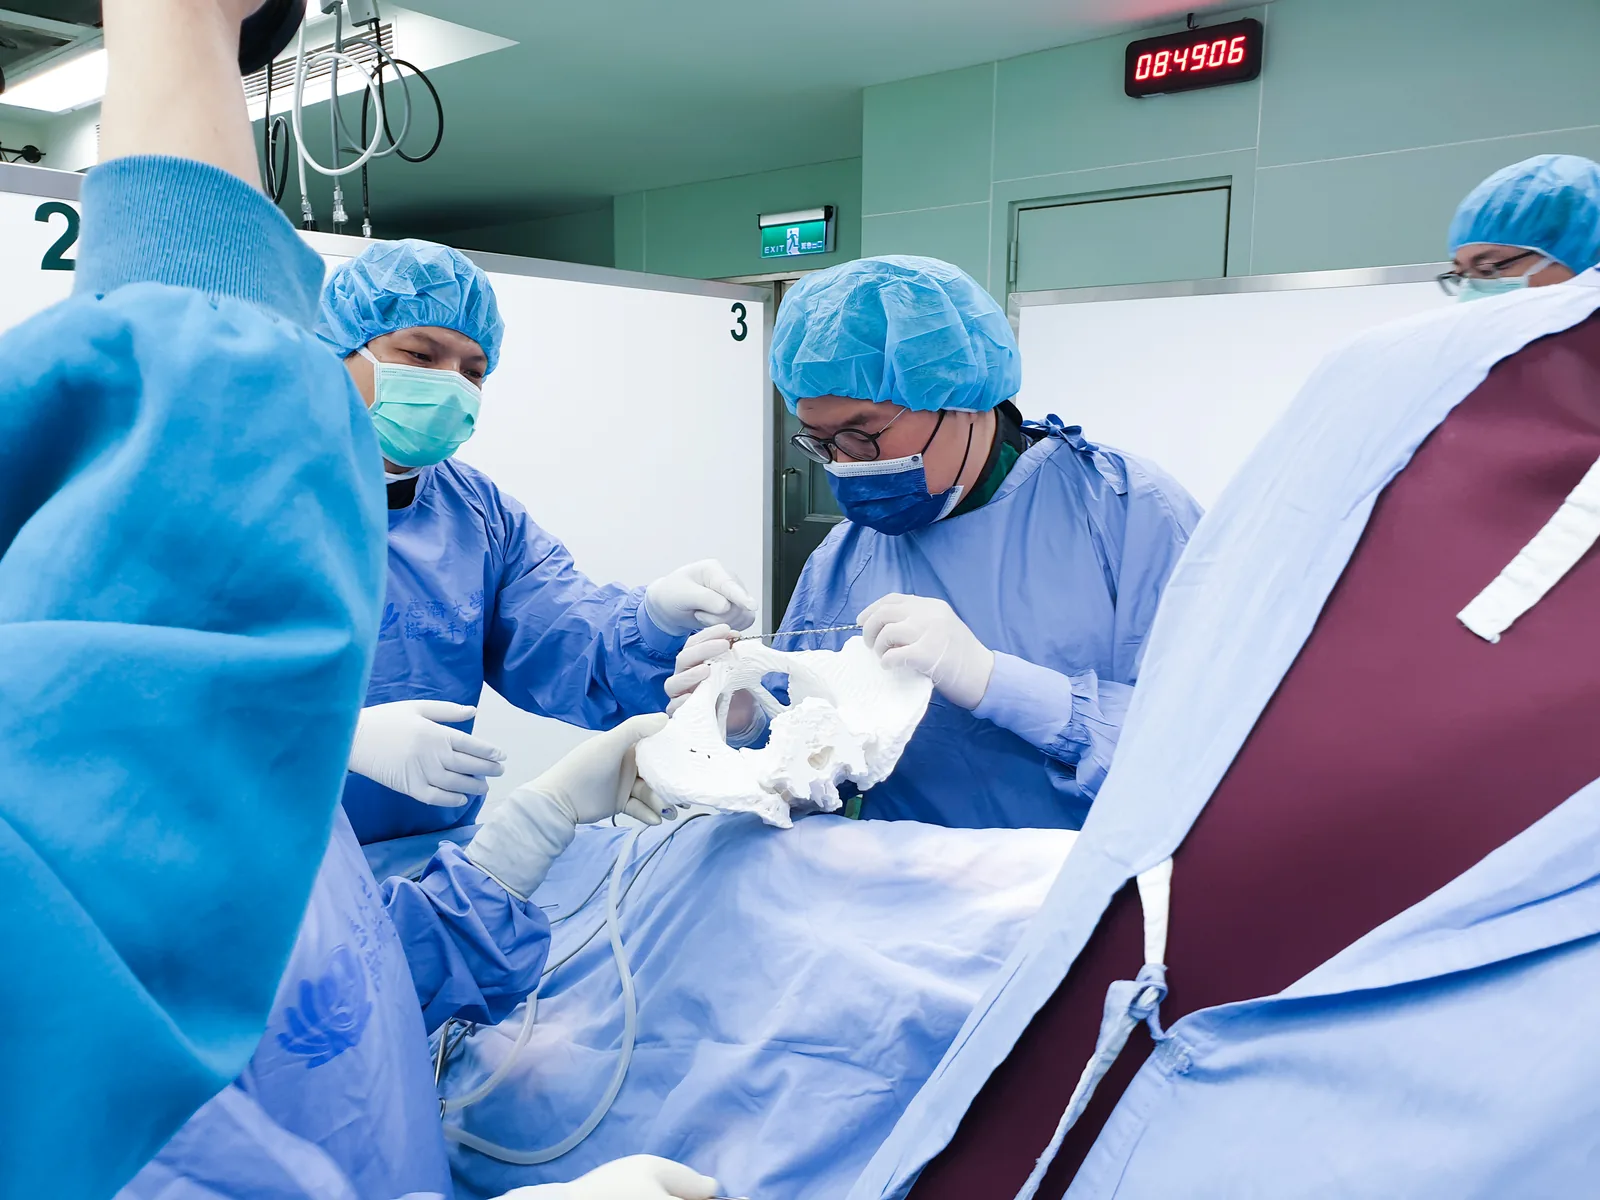
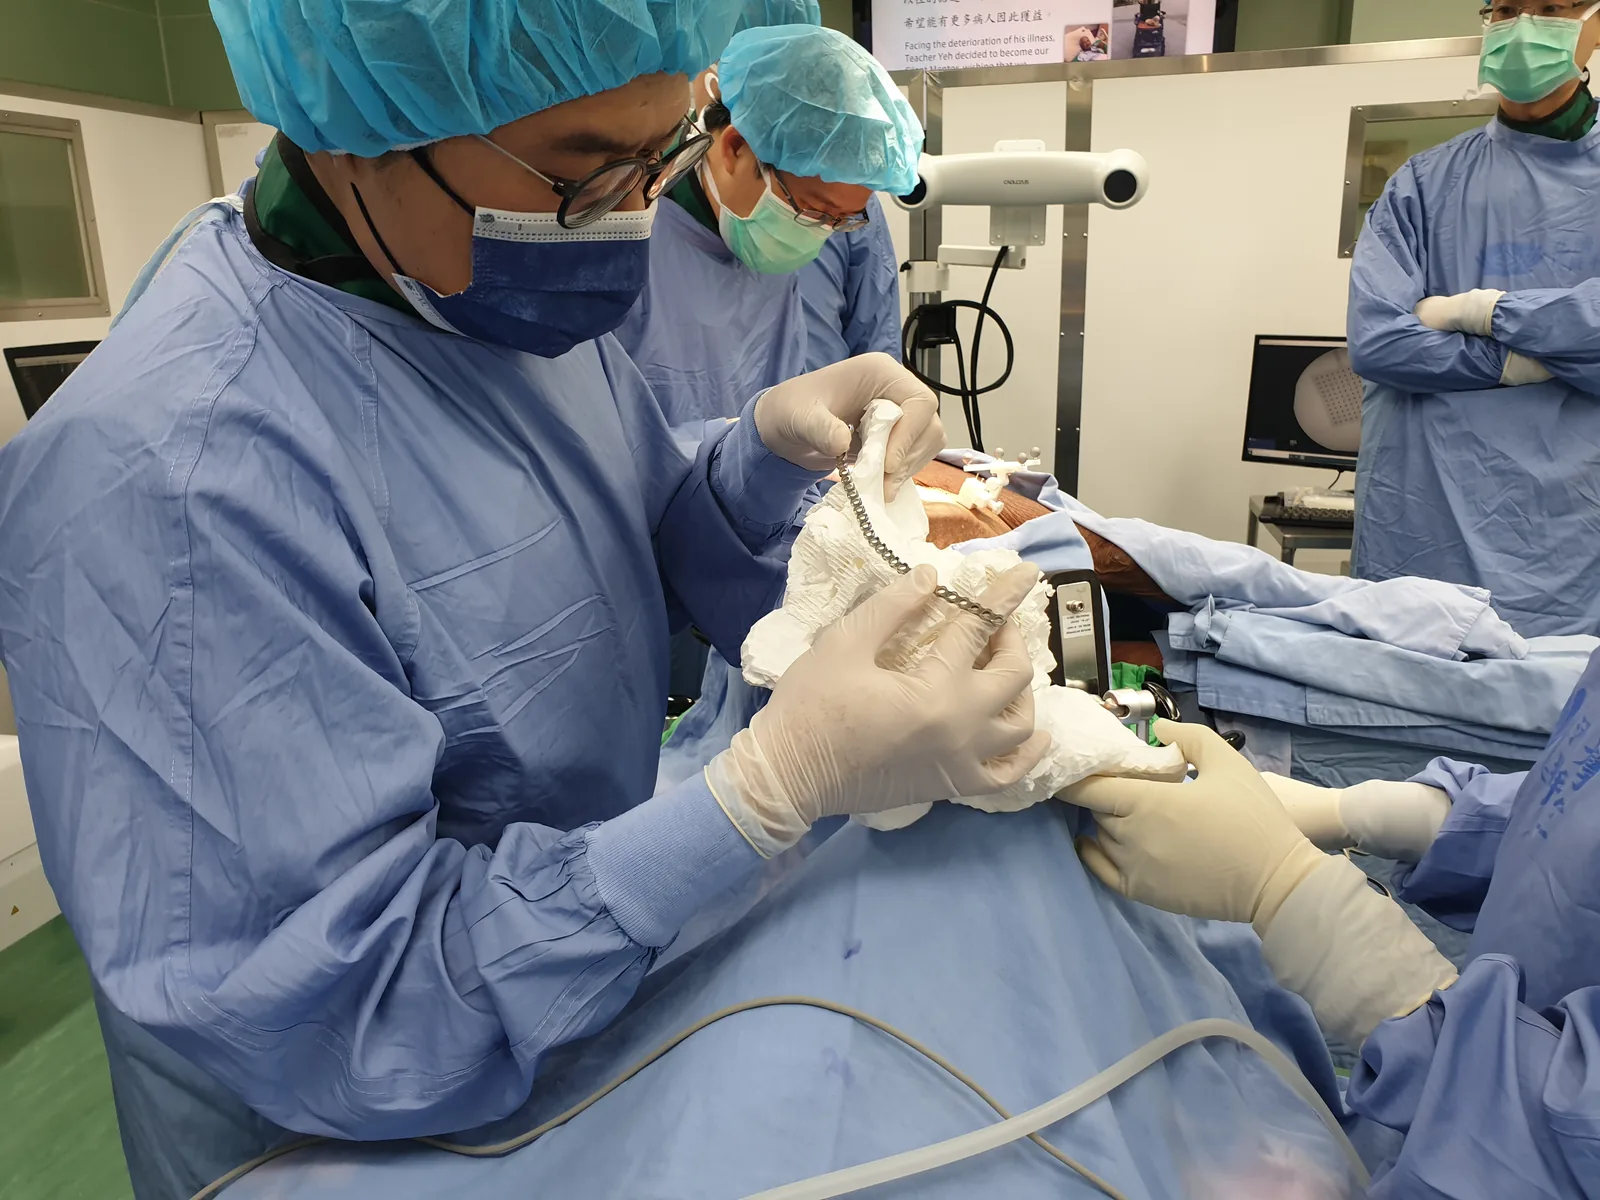
The photograph alongside is a real case. The scrubbed surgeon is holding a printed pelvis taken from that patient's own scan and shaping the fixation plate against it, on the sterile field, seconds before it goes in.
Patient-specific hardware
Implants, plates and guides are designed to one patient's anatomy.
Planning and training
The same printed models can be used to rehearse a procedure, and as a teaching tool.
Beyond orthopedics
The same workflow, other specialties
Bone is where OOOPDS started, but a DICOM data set is a DICOM data set. Cardiology uses printed hearts to plan valve replacements and rehearse catheter work; dentistry prints models for implant placement and orthodontic treatment; neurosurgery prints skulls for tumour and spinal work; and custom implants and prosthetics are designed to one person's measurements. OOOPDS can produce heart models from DICOM data in the same way it produces bone.
Customized bone plate
Plate design from the patient's own anatomy
Every skeleton is different. OOOPDS designs the plate on the reduced fracture, then hands it to the printer.
Designed on the fracture, not on the table
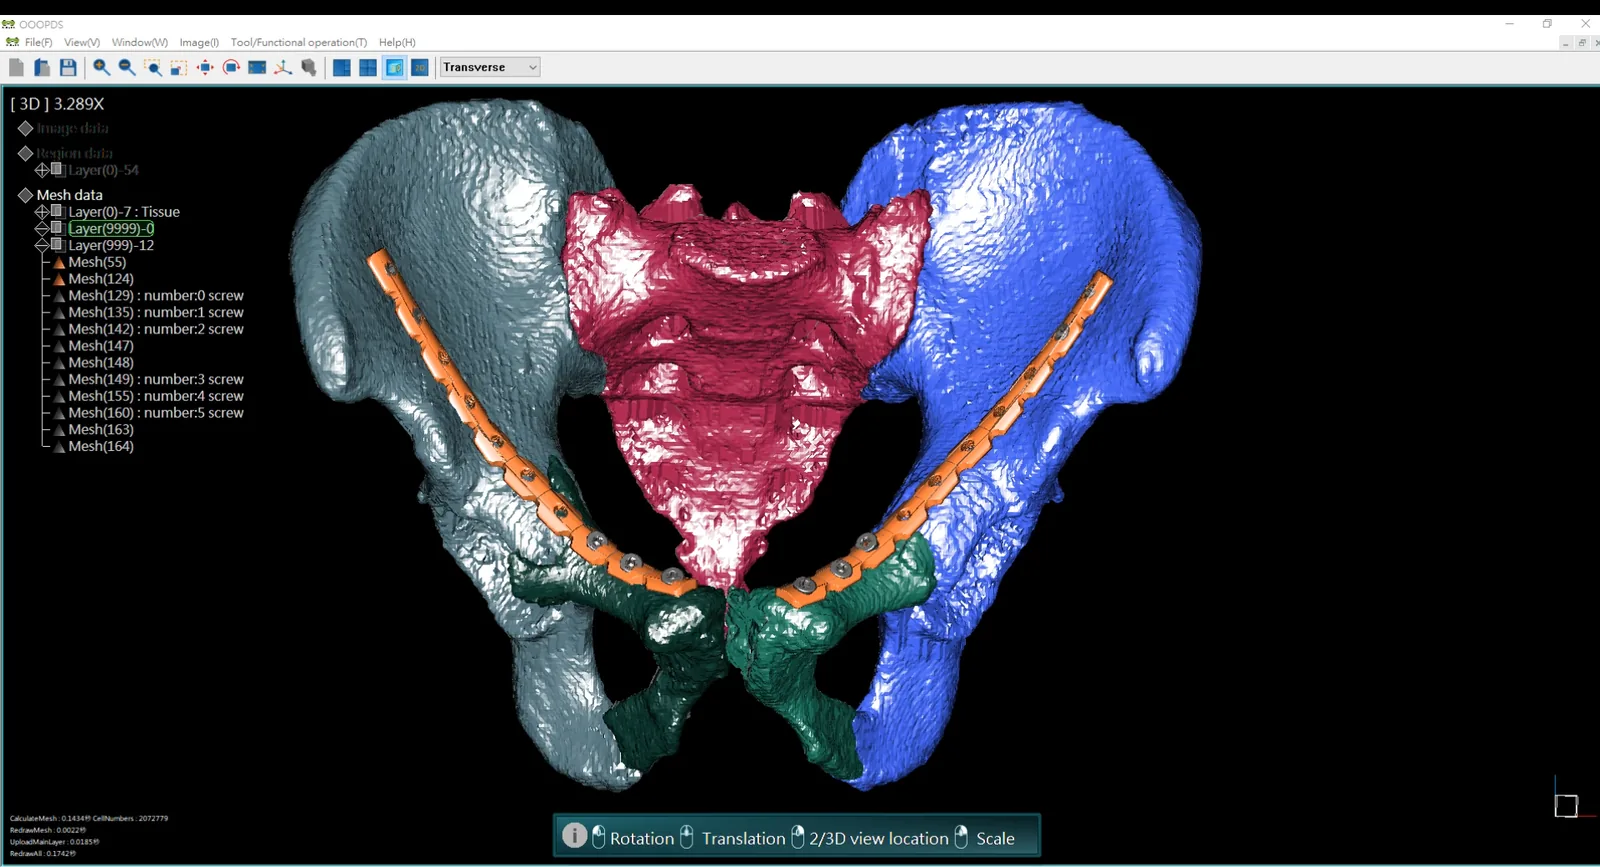
Patient DICOM data is imported and converted to 3D, the fracture is reduced in simulation, and the plate's shape, size and length are drawn onto the result with its fixation points chosen for stability. What comes out is a plate, or a template to bend a plate against, based on the reduced bone.
Fracture fixation
Complex fractures where a standard plate does not follow the shape of the bone.
Joint reconstruction
Repairs to a joint or a bone surface, where the fixation has to match a shape that carries load in a particular way.
Pelvic and spinal fixation
Fixation planning for the pelvis and the spine.
Clinical applications
Three specialties, one planning system
The imaging chain is the same wherever the operation happens: DICOM in, a scaled 3D model out, a simulated plan on top of it. What changes is what the surgeon is planning — a fracture, a trajectory through the spine, or an implant in a jaw.
Orthopedics
Preoperative planning for skeletal trauma: fracture patterns read on 2D and 3D reconstructions, reduction strategies simulated manually or by symmetry, screw paths and plate placement decided in advance, and custom plates exported for printing. Fracture management, trauma reconstruction, pelvic fixation and SI screw locking all run through the same workflow.
Neurosurgery
High-resolution imaging turned into detailed 3D models of complex structures, then used to plan pedicle screw placement and spinal puncture paths on that patient's anatomy.
Dentistry
CBCT data reconstructed in 3D for tooth position, impacted third molars and jawbone assessment, then virtual implant placement with angulation, depth and proximity to critical structures checked before surgery. Planning works backwards from the intended prosthetic result.
Interested in OOOPDS?
Send us a case and we will plan it with you
Bring a DICOM data set to the demonstration — a fracture, a spine, a jaw — and we will take it through import, reduction, implant simulation and the printable plate on screen, so you can judge it on your own imaging rather than on ours.